
Tuesday, March 27, 2012

VITAMIN C and CANCER

"...it takes much more than logic and clear-cut demonstrations to overcome the inertia and dogma of established thought." — Irving Stone

Irving Stone was an early thinker and writer about vitamin C (its scientific name is ascorbic acid). He knew it would be an uphill battle to change the way the medical profession viewed vitamin C. While most doctors accept that scurvy is a vitamin C deficiency illness, few have made the rather humongous jump to seeing high dose intravenous vitamin C as a major player in the management of cancer. 

There is actually a wide spectrum of medical uses for vitamin C. Evidence exists documenting it as the best antiviral agent now available ... IF used at the proper dose. Vitamin C can neutralize and eliminate a wide range of toxins. Vitamin C will enhance host resistance, greatly augmenting the immune system's ability to neutralize bacterial and fungal infections. Now the National Institutes of Health has published evidence demonstrating vitamin C's anti-cancer properties. With so many medical benefits, why do so few doctors know of them? 

One explanation stems from ascorbic acid's designation as a "vitamin." Consider Dorland's Illustrated Medical Dictionary's definition of vitamin: A general term for a number of unrelated organic substances that occur in many foods in small amounts that are necessary in trace amounts for the normal metabolic functioning of the body. As a vitamin, only a minuscule 60 mg of ascorbic acid is needed to prevent the emergence of scurvy symptoms. As a medical treatment for cancer and life-threatening infections and toxic exposures, tens of thousands of milligrams of ascorbic acid must be administered, often by the intravenous (IV) as well as the oral route. 

The Center's founder, Dr. Hugh Riordan, was a true scientist who believed in the power of scientific measurement over dogma. With the establishment of The Center in 1975, he routinely checked plasma vitamin C levels in chronically ill patients. He found these sick patients to be consistently low in their plasma C levels. Interestingly enough, the cancer patients he was seeing had VERY LOW vitamin C reserves. This matched scientific literature documenting low vitamin C levels in cancer patients. Cancer cells were actively taking up vitamin C in a way that depleted tissue reserves of C. 

PET scans are commonly ordered by oncologists to evaluate their cancer patients for metastases (cancer spread to other organs). What is actually injected into the patient at the start of the scan is radioactive glucose. Cancer cells are anaerobic obligates, which means they depend upon glucose as their primary source of metabolic fuel. Cancer cells employ transport mechanisms called glucose transporters to actively pull in glucose. 

In the vast majority of animals, vitamin C is synthesized from glucose in only four metabolic steps. Hence, the molecular shape of vitamin C is remarkably similar to glucose. (Figure 1) Cancer cells will actively transport vitamin C into themselves, possibly because they mistake it for glucose. Another plausible explanation is that they are using the vitamin C as an antioxidant. Regardless, the vitamin C accumulates in cancer cells.
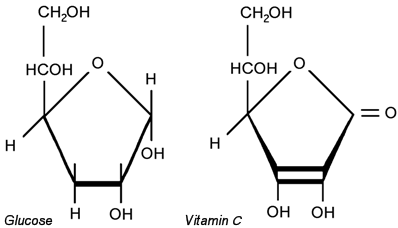


Figure 1
If large amounts of vitamin C are presented to cancer cells, large amounts will be absorbed. In these unusually large concentrations, the antioxidant vitamin C will start behaving as a pro-oxidant as it interacts with intracellular copper and iron. This chemical interaction produces small amounts of hydrogen peroxide.

Because cancer cells are relatively low in an intracellular anti-oxidant enzyme called catalase, the high dose vitamin C induction of peroxide will continue to build up until it eventually lyses the cancer cell from the inside out! This effectively makes high dose IVC a non-toxic chemotherapeutic agent that can be given in conjunction with conventional cancer treatments. Based on the work of several vitamin C pioneers before him, Dr. Riordan was able to prove that vitamin C was selectively toxic to cancer cells if given intravenously. This research was recently reproduced and published by Dr. Mark Levine at the National Institutes of Health.

As feared by many oncologists, small doses may actually help the cancer cells because small amounts of vitamin C may help the cancer cells arm themselves against the free-radical induced damage caused by chemotherapy and radiation. Only markedly higher doses of vitamin C will selectively build up as peroxide in the cancer cells to the point of acting in a manner similar to chemotherapy. These tumor-toxic dosages can only be obtained by intravenous administration.

Over a span of 15 years of vitamin C research, Dr. Riordan's RECNAC (cancer spelled backwards) research team generated 20 published papers on vitamin C and cancer. RECNAC even inspired its second cancer research institute, known as RECNAC II, at the University of Puerto Rico. This group recently published an excellent paper in Integrative Cancer Therapies, titled "Orthomolecular Oncology Review: Ascorbic Acid and Cancer 25 Years Later." RECNAC data has shown that vitamin C is toxic to tumor cells without sacrificing the performance of chemotherapy.

Intravenous vitamin C also does more than just kill cancer cells. It boosts immunity. It can stimulate collagen formation to help the body wall off the tumor. It inhibits hyaluronidase, an enzyme that tumors use to metastasize and invade other organs throughout the body. It induces apoptosis to help program cancer cells into dying early. It corrects the almost universal scurvy in cancer patients. Cancer patients are tired, listless, bruise easily, and have a poor appetite. They don't sleep well and have a low threshold for pain. This adds up to a very classic picture of scurvy that generally goes unrecognized by their conventional physicians.

When Center cancer patients receive IVC, they report that their pain level goes down, and that they are better able to tolerate their chemotherapy. They bounce back quicker since the IVC reduces the toxicity of the chemotherapy and radiation without compromising their cancer cell killing effects. IVC is complementary to oncologic care. IVC is not "either/or" - it's a good "both/and" proposition. IVC can help cancer patients withstand the effects of their traditional therapies, heal faster, be more resilient to infection, develop a better appetite, and remain more active overall. These things promote a better response to their cancer therapy.

IVC has been used for three decades here at The Center. There have been no serious complications, but there are a couple of potential complications that need to be screened for. Because vitamin C enhances iron absorption, iron overload must be ruled out. The high sodium load of IVC can create a fluid overload in a patient with congestive heart failure, renal insufficiency or failure. We also check our patients for G6PD deficiency (an enzyme used to maintain stability of the red blood cell membranes). Although many physicians worry that large doses of vitamin C may cause kidney stones, we have rarely seen the phenomenon, and several huge clinical trials in the medical literature refute this misconception.

To summarize, most organisms make their own vitamin C. When they are under stress, either by illness or injury, Mother Nature has provided them with a means to facilitate healing: they synthesize more ascorbic acid. As a result, they are in less pain, they remain active, they can sleep, and they have a better appetite: all functions which promote healing.
Dr. Riordan once said that here at The Center, we don't treat cancer... we treat people who happen to have cancer. IVC is a tool that allows our Center physicians to harness a healing mechanism that our human ancestors lost long ago: the ability to dramatically increase tissue levels of vitamin C. Research shows that the astonishingly high levels achievable only by IVC not only help fight the risk of infection and the pain of metastases, they actually aid in the defeat of the cancer cells themselves, through a very elegant mechanism that does no harm to healthy cells. It's a discovery that the medical world is only beginning to discover.

Source: http://scientifichealthjournal.blogspot.com/2012/03/intravenous-vitamin-c-and-cancer.html

High Daily Intake of Ascorbic Acid

Frederick Robert Klenner, B.S., M.S., M.D., F.C.C.P., A.A.F.P., after graduating Duke University School of Medicine, March, 1936, took three years of hospital training and then entered the private practice of medicine at Reidsville, N.C. Although specializing in diseases of the chest, Dr. Klenner is engaged in a limited general practice which has enabled him to make observations on the use of massive doses of ascorbic acid in virus diseases as well as on other pathological syndromes. He has published 28 scientific papers on these observations and has given numerous lectures to civic and other groups. Dr. Klenner is a Fellow of the American Association for Advancement of Science; Fellow and Diplomate of The International College of Applied Nutrition; Fellow of The Royal Society of Health, London, England; Honorary Fellow of The International Academy of Preventive Medicine and a member and fellow of many other medical and scientific organizations.

Introduction

The American Medical Association in its introduction to Nostrums, Quackery and Pseudo-Medicine states: “In from 80 to 85 per cent of all cases of human ailment, it is probable that the individual will get well whether he does something for his indisposition or does nothing for it. The healing power of nature, fortunately for biologic perpetuity, works that way.” These percentages are relative. Increased population and greater concentration in terms of living patterns, as well as other types of insult to the body, will frequently change this index. As physicians we have a duty to get the patient well, irrespective of his chance for self-healing with diet or herbs. Hippocrates once declared, “Of several remedies physicians should choose the least sensational.” Vitamin C would seem to meet this requirement.

The Virus Story

The common cold has received renewed interest since publication of Pauling’s book. [1] Brody, [2] in 1953, after studying vitamin C and its effect on colds in college students, advised that ascorbic acid be given early and often and in sufficient amounts. This confirmed what we had been experiencing and reporting over a period of several years. The response that we observed with massive and frequent doses of ascorbic acid in treating the common cold alerted us to the real significance of this treatment in preventive medicine. In February 1948, [3] I published my first paper on the use of massive doses of vitamin C in treating virus pathology. By February 1960, [4] some 25 scientific papers later, I realized that every head cold must be considered as a probable source of brain pathology. Many have died, especially children, following the sudden development of cerebral manifestations secondary to even a slight head and/or chest cold.

These insidious cerebral happenings are responsible for the so-called crib deaths attributed to suffocation. They die by suffocation, but by way of a syndrome similar to that found in cephalic tetanus toxemia culminating in diaphragmatic spasm, with dyspnea and finally asphyxia. These infants and children who have been put to bed apparently well, except for an insignificant nasal congestion, will demonstrate bilateral pneumonitis at autopsy. Adequate vitamin C, taken daily, will eliminate this syndrome. A similar pathology, dubbed Crib Syndrome, is less acute but unless recognized and treated heroically, the infant will also die. This condition is probably due to severe brain trauma received at time of delivery. Laryngismus stridulous will be present in this condition and the child will sound as if it has a cold. Calcium gluconate and massive, frequent injections of vitamin C will also reverse this pathology. The recognized treatment is daily oral dihydrotachysterol.

Adequate ascorbic acid taken during the period of gestation will also prevent the occurrence of this syndrome. The information relative to crib syndrome is backed by case histories at Annie Penn Memorial Hospital, Reidsville, N. C. I have seen children dead in less than two hours after hospital admission, having received no treatment, simply because the attending physicians were not impressed with their illness. A few grams of ascorbic acid, given by needle, while they waited for laboratory procedures or examination to fit their schedule, could have saved their lives. I know this to be a fact because I have been in similar situations and by routinely employing ascorbic acid have seen death take a holiday.

In a paper titled “An Insidious Virus,” [5] I reasoned that it should be a maxim of medicine for large doses of vitamin C to be given in all pathological conditions while the physician ponders his diagnosis. The wisdom of this dictum is backed by many hundred cases under our supervision. I have seen critically ill chest patients well enough to go home after intravenous injection of 1 or 2 liters of 5% dextrose in water, each carrying 50 gm ascorbic acid. This procedure resulted in a dramatic transition from sickness to health.

Virus encephalitis can also be associated with the common cold as a result of the presence of herpes simplex in cold sores. Lerner [6] and associates believe that thousands of cases exist yearly from this route. Of this number, they estimate that one third die; and of the survivors, eight out of nine have residual brain damage. Their work suggests that passive hemaggluting antibodies in the cerebrospinal fluid are a better indicator of the presence of infectious virus than are circulating antibody titers in the serum. The simple herpes virus from the insignificant fever blister, but possessing the capability of producing encephalitis, can remain hidden for years in the neuron according to Drs. Stephens and Cook. [7] This confirms the thinking of Goodpasture [ 8] given to us many years ago. Thus, a herpes simplex virus once present in a cold sore, although healed and leaving no evidence of lip pathology, could ignite later by simple exposure to ultraviolet light. How many mothers are endangering the lives of their children by sun-bathing, laboring under the belief that they are improving their health? Roizman [ 9] believes that all children are infected by age 5, but that only 1% experience true clinical illness. For many years investigators thought that each recurrence of fever blisters represented a new infection. Evidence is accumulating that shows the herpes simplex virus is harbored in dormant form until a physiologic or emotional event provokes the virus to produce the typical herpetic lesion. In one case with five repeats of herpes virus erupting at yearly intervals and at the same site, 7-10 gm ascorbic acid by mouth, daily, was found to eliminate this pathology.

Effecting a cure when a virus is the offending agent, and many times bringing about this change in the short space of 24 hours, is a rewarding moment in medicine. Vitamin C treatment must be intensive to be successful. Use veins when practical, otherwise give vitamin C intramuscularly. Never give less than 350 mg/kg body weight. This must be repeated every hour for 6 to 12 times, depending upon clinical improvement, then every two to four hours until the patient has recovered. Ice cubes held to the gluteal muscle before and after injection will reduce or eliminate pain and induration. When treatment continues for several days, the child can be placed on an ice cap between injections. When employing vitamin C intravenously, it is best to use sodium ascorbate and the solution free of all additives except sodium bisulfite. The dose of vitamin C using a syringe should range between 350 mg and 400 mg/kg body weight. In older patients or when very high doses are required the vitamin can be added to 5% dextrose in water, in saline solution or in Ringer’s solution. The concentration should approximately be 1 gm to 18 cc fluid. Bottle injections will need 1 gm calcium gluconate one to two times each day to replace calcium ions removed by the high intravenous schedule. One quart of milk daily will suffice when using the vitamin intramuscularly. In place of milk one can substitute calcium gluconate tablets.

Supplemental vitamin C is always given by mouth. As a guide in determining the amount and frequency of injections we recommend our Silver Nitrate-Urine test. [10] This is done by placing ten drops of 5% silver nitrate in a Wasserman tube and adding ten drops urine. A color pattern will develop showing white, beige, smoke gray or one that looks like fine grain charcoal. Charcoal is the color needed and the test is performed at least every four hours. The test itself is read in one minute.

These large doses of ascorbic acid will also bring all body tissue back to saturation which means that the white blood cells will now be capable of destroying other pathogens that might be clouding the picture. Unless the white blood cells are saturated with ascorbic acid they are like soldiers without bullets. Research on this is now under way at the Bowman Gray School of Medicine by McCall and Cooper. [11] White cells ingest bacteria and in the process produce hydrogen peroxide. Hydrogen peroxide will combine with ascorbic acid to produce a substance which is lethal to bacteria. I have seen diphtheria, hemolytic streptococcus and staphylococcus infections clear within hours following injections of ascorbic acid in a dose range of from 500 mg to 700 mg/kg body weight given intravenously and run in through a 20G needle as fast as the patient’s cardiovascular system would allow.

Part of the white cells are lymphocytes. They, too, play an important role in survival from infection. We found in several cases of trichinosis [12] that the behavior of the lymphocytes was the real story of the changing blood picture and actually determined the course of the disease. Wintrobe [ 13] observed that the function of the lymphocytes was stimulation of antibody formation and that the lymphocytic response runs parallel with the recovery of the patient. This build-up of antibodies appears directly proportional to the concentration of ascorbic acid in all body tissue, and yet we give vaccines but pay no attention to the degree of tissue saturation of ascorbic acid. Dr. Nossal [14] of the Institute of Medical Research, Melbourne, Australia, wonders about the mechanism by which lymphocytes, on meeting antigens, decide to be turned on or off. He asks what physiological mechanism underlies the discrimination between immunization and the induction of immunological tolerance and would suggest that it is controlled by vitamin C which in turn affects the negative charge which then influences the response of the lymphocyte. Ginter [15] of the Research Institute of Human Nutrition, Bratislava, offers some evidence to this effect in his statement: “that all reactions which are connected with vitamin C have oxidation-reduction features. It is therefore probable that the biological function of vitamin C can be located in the metabolic reactions which are connected with electron transfer.”

The killing power of ascorbic acid is not limited to just herpes simplex and the adenovirus. When proper amounts are used it will destroy all virus organisms. We found measles to be a medical curiosity. Specifically we observe that vitamin C given prophylactically, by mouth, was not protective unless 1 gm was given every two hours around the clock. One gram every four hours would modify the attack. One gram given every four hours intramuscularly was also protective. With our own children we kept the measle syndrome going off and on for 30 days by giving 1 gm every two hours for two days, then off for two days. The disease was then stopped by continuing 1 gm every two hours, by mouth, for four days. By 1950 we learned that we could kill the measles virus in 24 hours by giving intramuscular injections in a dose range of 350 mg/kg body weight every 2 hours. We also found that we could dry up chicken pox in the same time, but more dramatic results were obtained by giving 400 mg/kg body weight intravenously. Two to three injections in 24 hours were all that was required. We published these results in 1951. [16] Recently, we cured a man weighing 85 kg in four days taking 30 gm each day by mouth. In conclusion, the killing power of ascorbic acid on virus bodies has been demonstrated by me in hundreds of cases, many of which were treated in our hospital with nothing but vitamin C. We have published some 28 papers on this matter.

In certain individuals some virus conditions have a slower response. Herpes zoster and mumps belong to this group. We found that in these conditions equally rapid destruction of the virus could be effected through the use of adenosine-5-monophosphate. Adenosine was given according to age and weight, 25 mg in children and 50-100 mg intramuscularly in adults. This was given every 12 hours along with ascorbic acid. Adenosine will sometimes precipitate a mild reaction in that the patient will feel a fullness in his head with varying degrees of nausea.

Inhalation of aromatic spirits of ammonia will quickly relieve and, if used before injection, will prevent this condition. Their response, when adenosine was administered, led us to theorize that when a cell has been invaded by a foreign substance, like virus nucleic acid, enzymic action fostered by ascorbic acid contributes to the breakdown of virus nucleic acid to adenosine deaminase which converts adenosine to inosine. Some individuals cannot manufacture sufficient adenosine to cope with this phase of purine metabolism under certain stress conditions associated with virus pathology. The net result from this chemical action is to catabolize purines rendering them unavailable for making additional virus nucleic acid. Ascorbic acid is further unique in that it possesses the capability of entering all cells. After entering a virus infected cell, ascorbic acid proceeds to take up the protein coats being manufactured by the virus nucleic acid, thus preventing the assembly of new virus units. These newly made macromolecules within the host cell soon create a situation where the tensile strength of the cell membrane is exceeded with resulting rupture and cell death. Ascorbic acid, when given in the massive amounts that accomplish full tissue saturation, will also enter those cells harboring the so-called dormant virus.

Where the vitamin C removes the protective protein coat of the virus the micromolecule formed will act in the capacity of a repressor factor inhibiting further activity of the virus nucleic acid which is then destroyed by additional vitamin C. We offer as proof of this the instance of a patient having herpetic lesions for five years and being cured with continuous high daily intake of ascorbic acid. In acute virus infection, associated with a virusemia, ascorbic acid given intravenously will remove the protein protective coat from the virus body, leaving the denuded virus unit vulnerable to the leukocytes for destruction. Note that adrenal cortex extract and/or desoxycorticosterone acetate must also be considered for support of the adrenals in a debilitated patient.

The Cholesterol Story

Next in importance to the virus is the story of cholesterol. One must understand, as noted by Ginter [17], that acute scurvy and chronic hypovitaminosis C are metabolically different conditions. On this point the Food and Life Yearbook, 1939, U. S. Department of Agriculture, had this to say: “Even when there is not a single outward symptom of trouble, a person may be in a state of vitamin C deficiency more dangerous than scurvy itself. When such a condition is not detected, and continues uncorrected, the teeth and bones will be damaged, and what may be even more serious, the blood stream is weakened to the point where it can no longer resist or fight infections not so easily cured as scurvy.”

Working with guinea pigs many research groups have proved that acute avitaminosis C produces an increase m cholesterol concentration in the whole body. This increased concentration of whole body cholesterol in scorbutic guinea pigs can be caused either by increased biosynthesis or by slowed down cholesterol metabolism. The main pathway of cholesterol catabolism is in conversion to bile salts.

The stimulating effect of ascorbic acid on the oxidation of polyunsaturated fatty acids and decreased oxidation of linolenic acid in the tissues of scorbutic guinea pigs has been well documented. Mjasnikova [ 18] found that intravenous injections of high doses of ascorbic acid to patients with high level blood cholesterol is followed by a distinct decrease of cholesterolemia. It must be remembered that the referred high doses of vitamin C employed by other scientists does not approach the dose schedule that we recommend. For example, Tjapina [19] reported on the effect of intravenous doses of 500 mg ascorbic acid on cholesterolemia in patients suffering from atherosclerosis. The hypocholesterolemic effect from vitamin C was apparent within one hour. With continued daily injections of 500 mg there was continued drop in blood cholesterol. Spittle [20] showed that blood cholesterol levels, in humans, vary with the amount of vitamin C employed.

In our own experience we lowered the blood cholesterol in one patient 42 points in six weeks by increasing the vitamin C intake by mouth from 10 gm to 20 gm each day. Spittle advanced the theory that atherosclerosis is a long-term deficiency or negative balance of vitamin C, which permits cholesterol levels to build up in the arterial system and results in changes in other fractions of the fats. Ginter [21] also demonstrated that with a high cholesterol diet, guinea pigs used up all their dietary vitamin C while rats and rabbits who manufacture their own vitamin C showed a gain in ascorbic acid tissue levels. Ginter also showed that experimental animals given 50 mg vitamin C each day had cholesterol deposits 40% lower than animals fed the same diet but given only 5 mg of C daily. In a survey of 1000 school children Ginter et al showed that 97% suffered from vitamin C lack during winter months when C-rich fruits and vegetables were less abundant [22]. The children also showed corresponding rise in cholesterol. Czechoslovakian workers also reported that when guinea pigs are fed a diet deficient in vitamin C and rich in cholesterol, they frequently develop gallstones [23]. Small reported to the Society of University Surgeons in New Orleans in 1973 that when gallstones are removed from patients they are 60%-70% cholesterol [24].

This suggests a causative factor in human gallstone formation. Reviewing the literature and summarizing his own studies, Ginter concluded that there is no doubt that the daily intake of ascorbic acid in the control of cholesterol will have a more pronounced effect in those persons who are already saturated with vitamin C. Tjapina and many others have reported that when amounts of ascorbic acid as low as 500 mg each day, by needle, were continued for 60 days, the clinical picture in the majority of the patients was dramatic, especially concerning the manifestations of coronary artery disease. Willis [ 25] reported that in scorbutic guinea pigs, fatty deposits on the aorta were formed very quickly, even without adding cholesterol to their diet.

In 1957, Willis [26] found that when ascorbic acid was given to these scorbutic guinea pigs, the atherosclerotic lesions were quickly absorbed. Ascorbic acid is directly associated with the mechanism involved in the pathogenesis of human atherosclerosis. Duguid [27] found alterations of ground substance observed in atherosclerosis that produced experimentally to be morphologically similar. Electrocardiographic tracings by Shafer [28] on scorbutic animals showed that with prolonged vitamin C therapy, abnormalities disappeared entirely. Stamler [ 29], following the mortality rate for middle aged persons, found a significant drop with improved nutrition with supplemental C.

We must protect our heart from stress. Adequate vitamin C is one answer. Asahina and Asano [30] of the Toho University School of Medicine in Tokyo found that the larger the dose of ascorbic acid given to experimental rats, the longer they survived in decompression chambers in which the air was made to approximate that found at elevations of 33,000 feet. When ascorbic acid was given in amounts representing 14 gm in a human, only half their animals expired. In humans we have observed that 30 gm in 24 hours is critical in any acute situation. Had the Japanese doubled their vitamin C dose they probably would have had no deaths.

The Heavy Metal Story

Heavy metal poisoning is another morbid chapter in medicine. Lead poisoning comes from many sources. Auto exhaust, smelter furnaces and storage battery factories lead the list. Mercury takes second place. It is estimated that at least I million children in the U. S. have some degree of lead poisoning.

In 1964 Mokranjac and Petrovic [ 31] studied the effect of mercury chloride in guinea pigs when ascorbic acid was administered in different ways. They first gave each animal 200 mg of vitamin C a day for one week (this roughly would represent 14 gm in a human) and then administered a dose of mercury proved beforehand to be 100% fatal. They then continued to give 0.2 gm of vitamin C daily. After 20 days the animals were all alive proving that vitamin C had protected them from certain death. If they gave vitamin C before and none after poisoning, two died. If vitamin C was given daily after poisoning, nine of 25 died; and if a single massive shot was given after poisoning, eight of 25 died. This again confirms that high daily intake of vitamin C will protect one from many of the ills seen today. The same can be said for lead poisoning.

One of the more common types of lead poisoning is seen in long-term workers in lead storage battery plants. All have subclinical scurvy. Adequate ascorbic acid intake would eliminate the monthly blood examination for red cell stippling. The report by Dannenberg [ 32] that high doses of ascorbic acid were without effect in treating lead intoxication in a child must be ignored, since his extremely high dose was 25 mg by mouth four times a day and one single daily injection of 250 mg of C. Had he administered 350 mg/kg body weight every two hours, he would have seen the other side of the coin.

Monoxide poisoning is another killer or crippler. Persons living in most American cities are frequently exposed to 100 ppm (that is, 115 mg/cu mm) of carbon monoxide in the ambient air for varying periods of time and may attain carboxyhemoglobin blood levels up to 10% [33]. Carboxyhemoglobin blood levels up to 7% have been reported in cigarette smokers. These levels of carbon monoxide are quite capable of causing considerable interference with tissue oxygenation in man by displacing oxygen from the hemoglobin molecule and shifting the oxyhemoglobin dissociation curve to the left. Anderson [ 34] reports a definite link between carbon monoxide, both in the atmosphere and in cigarette smoke, with cardiac function.

Normal coronary arteries can readily dilate and supply an increased demand; while diseased coronary arteries (e.g., angina pectoris) may not be able to meet this challenge. The hypoxic effect of carbon monoxide may act in a synergistic manner with other factors operative in ischemic heart disease, outstripping the limited coronary reserve and augmenting the production of stress-induced myocardial ischemia.

Interesting is the report by Pelletier [ 35] who has shown experimentally that once you stop smoking, your ascorbic acid level approaches that of the nonsmoker. Victims of house fires, especially children, succumb more often to monoxide poisoning, which is overlooked in the course of treating the burn. Mayers [36] warns physicians that symptoms of smoke poisoning might be delayed from 3 to 48 hours. In cases of this nature ascorbic acid serves a dual purpose.

A dose of 500 mg/kg body weight of vitamin C given intravenously will immediately neutralize the carbon monoxide or smoke poisoning while at the same time it will prevent blood sludging which is a major factor in the development of third degree burns.

Other Applications

Other therapeutic effects of vitamin C include the following. Vitamin C will also destroy pseudamonis, locally as a 3% spray and systemically with massive frequent injections. This has been demonstrated in case histories on burns treated at Annie Penn Memorial Hospital, Reidsville, N. C. It is a demonstrated principle that the production of histamine and other end products from deaminized cell proteins, released by injury to cells, is a cause of shock.

The clinical value of ascorbic acid in combating shock is explained when we realize that the deaminizing enzymes from the damaged cells are inhibited by vitamin C. Chambers and Pollock [ 37] have reported that mechanical damage to a cell results in pH changes which reverse the cell enzymes from constructive to destructive activity. The destructive activity releases histamine, a major shock-producing substance. Ascorbic acid, when present in sufficient amounts, inhibits this enzyme transition.

Ascorbic acid will reverse shock found in other areas of medicine. In one patient who had taken 2640 mg Lotusate (talbutal), the blood pressure was 60/0 when first seen in the emergency room. Twelve gm sodium ascorbate was administered with a 50 cc syringe. In ten minutes the blood pressure was recorded at 100/60. Over 100 additional grams were given intravenously over the following three hours, at which time the patient was awake. Shock from toxalbumin, neurotoxin, proteotoxin, muscarine and formic acid responds equally as well to high doses of vitamin C. Keeping the tissues saturated will prevent such experiences or make recovery by additional vitamin C a routine matter.

Blumberg, writing in Medical World News, noted that the discovery of the Australian antigen raises hopes for an effective hepatitis vaccine. Many controversial studies have been reported in the use of this antigen. Another controversial substance, vitamin C, will cure viral hepatitis in two to four days and allow the patient to immediately resume his usual activities.

It should be given in a dose range of 500 to 700 mg/kg body weight every 8 to 12 hours. Our latest case was given 5 gm sodium ascorbate, as crystals dissolved in 200 cc water or fruit juice, every 4 hours — i.e., 30 grams per 24-hour period. All symptoms and signs were removed in 96 hours. By contrast treating virus hepatitis with an immunizing agent would possibly require several vaccines in a single hepatic epidemic. If you want results, use adequate ascorbic acid.

The Cancer Story

The question of virus and cancer association is still academic. Herpes simplex causing cervical cancer appears to be positive. We have cured many fever blisters by applying a 3% ointment of vitamin C to the lip 10-15 times a day. This is put in a water soluble base.

I think that it is time for those women with a family history of cervical cancer to douche with a 3% solution of ascorbic acid at the first report of cervical erosion. Tamponing with a 3% solution should also be done by the physician. Twenty grams of vitamin C daily by mouth along with local application of vitamin C could erase this form of malignancy.

Virus and breast cancer, which in the mouse has been established, seems likely to be confirmed in women on the basis of a hereditary factor along with a virus role. Paul Broca (1866) pointed out that ten of 24 women among his immediate forebears had died of cancer of the breast. J. A. Murray (1911) demonstrated that mice with familial history of breast cancer developed breast cancer at an incidence three times that of mice with no familial history of tumor. Feller and associates found particles resembling type B and C viruses in eight of 16 human milk specimens from women with breast cancer but in only one of 43 apparently cancer-free women. These are stepping stones which serve to give warning that women from cancer-prone families should not breast feed their children. What will daily high intake of vitamin C do in altering the breast cancer picture? The answer is waiting for experimental work to be done with mice from knowledge gained from Bittner’s classic cross-suckling experiment.

The role of ascorbic acid in treating virus cancer pathology can be seen with its action in mononucleosis. Large doses of vitamin C, given intravenously, will eliminate this virus in just a few days, the actual time being directly proportional to the amount of the vitamin employed in relation to the severity of the infection. A research team at Yale, after studying hundreds of college students, believe they have evidence that associates the Epstein-Barr virus with Burkett lymphoma [38, 39]. This has also been confirmed by researchers at Children’s Hospital, Philadelphia, Pa.

Many investigators have been working with immunological procedures for the treatment of malignant disease. As we noted earlier, unless the patient’s tissues are saturated with vitamin C, the response in this area will be negated. Massive employment of vitamin C will make possible prolonged radiation therapy in late cases. It will also prevent radiation burns. Who can say what 100 gm or 300 gm given intravenously, daily, for several months might accomplish in cancer.

The potential is so great and the employment so elementary that only the illiterate will continue to deny its use. Schlegel [ 40] has demonstrated that the use of ascorbic acid as low as 1.5 gm each day will prevent recurrence of bladder cancer. This is the so-called wasted vitamin C.

Other Applications

Rous [41] has found that just 3 gm daily, by mouth, for four days will completely relieve all symptoms of urethritis. He believes that the urethral irritation is caused by phosphatic crystals formed in the urine because of insufficient acidity. Ascorbic acid, in this case, acidified the urine enough to force the crystals back into solution. The neglected chronic cystitis which is the rule with ammonical decomposition in the bladder, most always associated with marked alkalinity of the freshly voided urine, will cease to be a clinical entity once people take at least 10 gm vitamin C every day. This will also eliminate the backwash type pyelitis so debilitating, especially in women of childbearing age.

In over 300 consecutive obstetrical cases, we found that the simple stress of pregnancy increased the ascorbic acid demand up to 15 gm daily. This simple stress of pregnancy becomes meaningful when we review the work of Conney [42] on mammalian synthesis of vitamin C in the rat. Compared to a 70 kg individual the rat would make, under stress, 15.2 gm of C each day.

Compare this to the 100 mg now recommended in pregnancy by the National Academy of Science and National Research Council and the disparity is shocking. Fred Stare’s 40 mg/day is catastrophic. This must be changed. There are at least 16 categories [42], not including scurvy, that cry out against minimal daily requirements for vitamin C. There can never exist a situation where a set numerical unit of vitamin C will meet the needs of all men. This is true because people are different and these same people experience different situations at various times. Roger Williams, speaking before the National Academy of Science in 1967, reported that among guinea pigs living in his laboratory, some needed 20 times more vitamin C than others to maintain health.

We must accept Ginter’s conclusion that acute scurvy and chronic hypovitaminosis C are metabolically different conditions. Antonowicz and Kodicek (1969), working with guinea pigs, discovered an extremely complex chemical process existing in animals receiving ascorbic acid which did not occur in the animals with scurvy. They found that glucosamine synthesis with the formation of galactosamine was normal in those animals receiving vitamin C but did not take place in those with scurvy.

Under a grant from the National Institute of Mental Health, Hepler and associates, according to Medical Tribune, reported that marijuana smoking caused a significant decrease in intraocular pressure. This decrease was found 30 minutes after smoking. In fine print they conceded that the drop was not significant after three hours. Thus, one would need be a chain-link smoker to maintain worthwhile levels [ 43, 44]. No mention was made of the many deleterious effects smoking marijuana has on the human body.

Virno and associates [45], working in G. B. Bietti’s eye clinic observed a pronounced reduction in intraocular pressure in the glaucomatous eyes by giving high daily doses of vitamin C. Bietti states that these high doses of vitamin C are a very effective hypotonic agent for intraocular pressure and when an intravenous dose calculated at 1 gm/kg body weight is administered, the action is predominantly by osmotic dehydration of the eyeball. Virno employed 35 gm by mouth in divided doses each day. This gave marked reduction of pressure within four hours and this was maintained even in patients where Diamox and Philocarpone had failed.

Linner in several symposiums using 0.5 gm twice daily reported no significant changes in eye pressure. Linner used 1 gm and Virno 35 gm each day — thus the difference in results. In the 1940s patients died receiving 5,000-10,000 units penicillin every four to six hours. The same type pathology is cured today in 24 to 48 hours using 1-3 million units. The size of the dose does make a difference — a real difference.

Dr. Linus Pauling has written that “Biochemical and genetic arguments support the idea that orthomolecular therapy may be the preferred treatment for many ill patients.” It is difficult to understand why megavitamin therapy remains so controversial when massive doses of vitamin B12 are universally used in pernicious anemia and niacinamide to correct the pathology of pellagra. I have used 150,000-200,000 units of vitamin A in a case of ichthyosis. The patient has been taking this dose for ten years. His skin is clear with no signs or symptoms of vitamin A toxicity. During the same time he has taken 10 gm of vitamin C each day. Is vitamin C the answer?

Hoffer [46] and Osmond were probably the first to realize the value of ascorbic acid as an adjuvant with niacin in treating schizophrenics. They employed from 6 to 8 gm daily. One acute case was given 1 gm every hour for 48 hours at which time the patient was completely recovered and remained so for six months without further treatment.

 Hawkins [47] found that by adding megavitamin treatment he doubled the recovery rate, half the rehospitalization rate and virtually eliminated self-destruction in dealing with schizophrenics who have a suicide rate 22 times that of the general population.

Dr. Pauling enabled his clinic to treat seriously ill schizophrenics for $200 per patient per year and to reduce the number of patient visits from 150 per year to 15. Hawkins’ method gives schizophrenic patients four gm ascorbic acid and four gm niacin or the equivalent in niacinamide, in divided doses, each day. Vanderkamp (1966) demonstrated that schizophrenics burn up ascorbic acid ten times faster than normal people. On an intake of four gm vitamin C each day, almost 100% of normal people will spill some degree of ascorbic acid into the urine.

In schizophrenics one can often go as high as 40 grams/day before spilling occurs. I have observed this same picture in severe virus infections where the patient did not spill over the urine until the second or third day, when a clinical response was evident. Milmer in Great Britain and Lucksch in Germany have reported significant improvement in schizophrenics given vitamin C alone. Both investigators used the double blind approach.

Ascorbic acid has value as an adjuvant in other medical syndromes. With para-aminobenzoic acid (PABA), which is a fraction of the B vitamins, it will cure trichinosis in nine days [48]. Used with intravenous mephenesin or methocarbamol, it will cure tetanus in 96 hours.

Arthritis is not only a crippler but also a nagger. Aspirin is the favorite medication of many physicians because it will ease the arthritic pain. This makes aspirin a good guy and a bad guy. The bad side is that those who take high aspirin therapy will also have low platelet and plasma levels for vitamin C. With low plasma levels there will also be depletion in the white blood cells. We know what this will do. As to platelets, their main business is to keep people from bleeding to death. When a blood vessel ruptures, collagen tissue, which makes up the basement membrane of blood vessels, is exposed.

The collagen affects the platelets so that they release a mineral substance called adenosine diphosphate. This substance makes the platelets very sticky so that they cling together. Aspirin can destroy this substance, but adequate vitamin C will prevent this action. As the platelets act to seal off the wound, a second mechanism for clot formation comes into play. This is a liquid protein called fibrinogen. In a recent case in which the platelet count was abnormally low and bleeding was a serious problem, 25 gm of ascorbic acid daily by mouth raised the platelet count back to normal with cessation of bleeding.

Vitamin C is also the number one agent in collagen formation. A person who will take 10-20 gm of ascorbic acid a day along with other nutrients might very well never develop arthritis. Abrams and Sandson [49] have pointed out that synovial fluid becomes thinner, thus allowing easier movement, when serum levels of ascorbic acid are high. Drugs such as ACTH and cortisone are noted for their ability to drain ascorbic acid in prolonged usage. In our experience we found that the patient who took vitamin C to tolerance made more rapid progress in reversing arthritic joints.

 The importance of daily high intake of ascorbic acid in preventive medicine has no limits. Crest and Colgate might limit tooth decay to one cavity every checkup, a relatively high index. Ten or more gm of ascorbic acid from age 10 up and at least 1 gm for each year of life, each day, through age 9 will record no cavities. Our son who is 20 has never had a tooth cavity. The same schedule could eliminate disc pathology.

McCormick believes the problem is avitaminosis C [ 50]. Greenwood [ 51] believes that adequate amounts of ascorbic acid seem necessary to disc metabolism and maintenance. In surgery we found that plasma determinations taken before starting anesthesia, at the conclusion of surgery, and six hours later, were constant. At 12 hours postoperative, there was a significant drop in vitamin C levels and at 24 hours there was a dramatic loss of the vitamin. We have always required the surgeon to give 10 gm before surgery, 10 gm in each postoperative bottle of fluids and 10 gm by mouth after discontinuing fluids. Crandon et al state that postoperative disruption of abdominal wounds occurs eight times more often in patients with vitamin C deficiency.

Not only surgery but any type of wound or fracture will heal slowly or not heal at all without the benefits of adequate vitamin C. Powdered vitamin C mixed with water to form a paste and applied to poison ivy or oak will usually effect a cure in 24 hours when adequate vitamin C is also taken by mouth. Ascorbic acid does have a definite influence on the rheumatic heart, especially in the acute stage [52].

I have seen children with the heart impulse so great that it raised the bed covers with each contraction recover so completely that later in life they were inducted into the armed services.

Massive daily doses will also cure tuberculosis by removal of the organisms’ polysaccharide coat.

It does the same with pneumococci. I am convinced that ten or more grams a day will prevent cancer of the lung in tobacco smokers.

It will relieve prickly heat and prevent heat stroke. Vitamin C will immediately reverse heat collapse, cramps or exhaustion if 12 to 40 gm are given intravenously.

It will bring recovery to electric shock victims if sufficient amounts are administered soon after the accident. Lightning victims can also be saved. I have done it.

Chronic myelocytic leukemia responds dramatically to 30 or more grams daily by mouth. Pancreatitis can be cured in less than three hours with 50 gm intravenously, and ten gm daily by mouth is positive insurance that it will never return.

Virus pancarditis as a sequela of an adenovirus infection can be relieved in 36 hours giving 400 mg/kg body weight, intravenously, every four to six hours. I have never seen a patient that vitamin C would not benefit. And, too, never send a boy to do a man’s job; meaning the dose level is very important.

In closing, I would like to quote Herbert Spencer, who summed up rather well a caution I would like all of us to take to heart: “There is a principle which is a bar against all information, which is proof against all argument, and which cannot fail to keep a man in everlasting ignorance. That principle is condemnation without investigation.”

Summary

The drug evaluation book of the American Medical Association (1971) gives information on the value of ascorbic acid which is at least 30 years behind present day knowledge. The 200-500 mg of ascorbic acid which is recommended as the 24-hour dose in burn cases is a typical example.

 From clinical experience we know that ascorbic acid must be given to burn victims in massive, frequent intravenous injections. Thirty to one hundred grams daily is the proper amount to employ and this is given until healing takes place — 7-30 days depending upon the degree of burn.

We have found and reported that this massive vitamin C therapy will eliminate skin grafting by keeping the tissues oxygenated. Ample supply of oxygen to the tissues will prevent blood sludging and in place of the third degree burns that develop on the fourth or fifth day, the eschars will drop off leaving normal tissue.

These high doses of ascorbic acid will also remove the smoke poisoning found in many fire victims and save many lives, especially children who expire from the effects of monoxide gas. The statement found in the A.M.A. book mentioned above — that controlled studies have shown no benefit from large doses of ascorbic acid in human subjects — must be ignored.

The large doses referred to never exceeded 5 gm and in most cases not more than that found in a quart of orange juice, for a 24-hour period. It is unfortunate that the editorial staff of the AMA failed to check out the world literature.

An example of their high doses was an article by Dannenberg [ 32] which was published in the JAMA in which the author found no value in lead poisoning by giving extremely high doses of ascorbic acid to a child. Dannenberg’s extremely high dose was 25 mg four times a day, by mouth, and one single intramuscular injection of 250 mg. Had Dannenberg employed 350 mg/kg body weight and given it, intramuscularly, every two to four hours he would have had a recovered patient in less than 72 hours.

The amount of ascorbic acid employed in any given case is the all important factor. In 28 years of research we have observed that 30 gm each day is critical in terms of response. This seems to be true regardless of age and weight.

In certain pathological conditions like barbiturate intoxication, snake bite or virus encephalitis, higher doses are required in some individuals. We have observed from experience and from review of the literature that 15%-20% of humans require much more ascorbic acid than do others.

Approximately 15% is in evidence when giving vaccines, since they make no antibodies.

Roughly 15% of pregnant humans were scheduled, in the past, to become paralyzed if hit with the polio virus.

Fifteen percent of over 3000 cases in our files required more ascorbic acid to prevent colds or to relieve the cold once infected. This percentage difference is the reason why one patient would die with pneumonia while another lived, when all other factors were apparently equal. This dosage factor alone has misled many scientists to disregard the value of ascorbic acid in virus pathology because they would see dogs die with distemper when they knew that the dog could make his own vitamin C. What they did not appreciate was that even the animal could not make enough vitamin C under certain situations. I have cured many dogs suffering with distemper by giving several grams ascorbic acid, by needle, every two hours.

We also found in over 300 obstetrical cases that roughly 15% require as much as 15 gm supplemental vitamin C each day just to remain within normal limits. Ten grams each day was the highest requirement of the other 85%.

Herpes simplex virus and the adenovirus can be destroyed with high doses of ascorbic acid. Many infections can be prevented by taking adequate vitamin C, daily, by mouth — 1 gm for each year of life up to age 10 and after 10 years of age at least 10 gm vitamin C daily. With these amounts the patient will spill varying amounts into the urine. The kidneys have a threshold for vitamin C much like the spillway of a dam. Spilling is necessary to assure adequate amounts for various body tissues. For example, white blood cells are useless unless they are full of ascorbic acid, since it is the ascorbic acid which makes their phagocytosis and/or destruction of pathogens possible. Although herpes simplex usually shows itself as a small lip sore and the adenoviruses as a mild but lingering cold, both can become killers through passage of the virus to the brain. Either one can cause crib deaths, which is truly the real cause. Again, we point out that high daily intake of vitamin C can prevent this tragic incident. For this reason, if for no other, the National Research Council and the National Academy of Science must remove the so-called minimal daily requirement for this substance.

Williams has shown and reported to the National Academy that even guinea pigs living in his laboratory differ in their requirements for vitamin C and that they differ each day, sometimes 20 times a given unit. Guinea pigs, like man, cannot manufacture ascorbic acid due to genetic fault. Scurvy which accounts for the thinking on the amount of vitamin C needed is actually of no consequence m terms of avitaminosis C, which can determine one’s future existence. Ginter, after ten years of research with vitamin C, concluded that acute scurvy and chronic hypovitaminosis C are metabolically different conditions. Antonowicz and Kodick confirmed this by finding that glucosamine synthesis in the guinea pig with the formation of galactosamine was normal in those animals receiving vitamin C but did not take place in the presence of acute scurvy.

Ascorbic acid when taken in sufficient quantities will relieve the intraocular pressure in the glaucomatous eyes, will relieve such things as prickly heat, and is a positive reversal for pemphigus.

Vitamin C when given by needle will destroy all viruses and many can be destroyed by taking 25-30 gm each day by mouth. Lesser amounts will protect against these pathogens.

I have cured diphtheria, hemolytic streptococcus and staphylococcus infections by employing vitamin C intravenously in a dose range of 500 to 700 mg/kg body weight. Doses under 400 mg/kg body weight can be given with a syringe using the sodium salt. This will always produce thirst. Fluids taken just before or immediately after will eliminate this annoyance. Doses above 400 mg/kg body weight must be diluted to at least 1 gm to 18 cc solution, using 5% dextrose in water, saline in water or Ringer’s solution. One gram calcium gluconate must be added to these bottle injections to replace Ca ions pulled from the calcium-prothrombin complex. There is no limit to the amount that can be administered by vein when honoring these two precautions.

The use of vitamin C in cancer will prove to be a very beneficial agent. We recommend bottle doses containing 60 gm vitamin C and such fractions of the B complex as 500 mg thiamin HCl, pyridoxine 300 mg, calcium pantothenate 400 mg, riboflavin 100 mg and niacinamide 300 mg. This is to be given daily or even twice daily.

Vitamin C is a positive neutralizing agent in snake bite [53], spider bite [54] and insect stings. Our use of ascorbic acid in snake bite has been limited to the Highland moccasin, a member of the copperhead family. Other poisonous snakes are more deadly but we can easily calculate from our experience what dose to employ. In a 4-year-old receiving a full strike from a mature Highland moccasin, 12 gm was required. Unlike a virus that will continue production until completely destroyed, the venom of the snake is constant in that there will exist no later increase in amount. I would suggest 40-60 gin, as a starter, in a large diamondback or cottonmouth. Additional vitamin C can be given if needed since the patient will be well on the road to recovery with the first injection.

Adenosine monophosphate given with ascorbic acid will increase the potential of the vitamin. This can be given in doses from 25 mg in children to as much as 200 mg in adults. Our use of this agent has been limited to mumps and herpes zoster but we are now of sufficient knowledge to believe that its use should be routine. The aqueous solution is more efficacious than the gel. Some patients experience a fullness in the head, a sickish feeling in the chest and a slowed pulse rate. Aromatic spirits of ammonia as a smelling agent relieves or prevents this syndrome. At present we are using 50 mg doses more frequently, until we can establish a reason for this type response.

Ascorbic acid can be lifesaving in shock. Twelve grams of the sodium salt given with a 50 cc syringe will reverse shock in minutes.

In barbiturate poisoning and monoxide poisoning the results are so dramatic that it borders on malpractice to deny this therapy.

Surgeons must learn to employ ascorbic acid more liberally. Ten to twenty grams in the preoperative solutions and 10 gm in each postoperative bottle will all but eliminate surgical deaths and will reduce hospital stay by 50%.

The same can be said for obstetrical cases. We found that obstetrical cases needed 4 gm each day the first trimester, 6 gm the second trimester and 8-10 gm the third trimester. Fifteen percent of the patients required 15 gm each day just to stay within normal limits.

Ascorbic acid is the safest and the most valuable substance available to the physician. Many headaches and many heartaches will be avoided with its proper use.

References

  1. Pauling, L.: Vitamin C and the Common Cold San Francisco: W. F. Freeman & Co., 1970.
  2. Brody, H. D.: J. Amer. Diet. Ass., 29:588, 1953.
  3. Klenner, F. R.: Virus pneumoniaand its treatment with vitamin C Southern Med. Surg., Feb. 1948.
  4. Klenner, F. R.: Encephalitis as a sequelae of the pneumonias. Tri-State Med. J., Feb. 1960.
  5. Klenner, F. R.: An insidious virus. Tri-State Med. J., June 1957.
  6. Lerner, M. et al: Detecting herpes encephalitis earlier. Med. World News, May 26, 1972.
  7. Stephens, J. C. and Cook, M. Cases of the hidden herpes virus. Med. World News, Feb. 25, 1972.
  8. Goodpasture, E. W.: Case of the hidden herpes virus. Med. World News, Feb. 25, 1972.
  9. Roizman, B. et al: Tracing herpes viruses. Med. World News, Oct. 1, 1971.
  10. Klenner, F. R.: A new office procedure for the determination of plasma levels for ascorbic acid. Tri-State Med. J., 5, 1956.
  11. McCall, C. E. and Copper, R.: Vitamin C shows promise as a bactericidal agent. Bowman Gray School Med. Med. Alumni News, 14:1, Feb., 1972.
  12. Klenner, F. R.: The treatment of trichinosis with massive doses of vitamin C and para-aminobenzoic acid. Tri-State Med. J., 1952.
  13. Wintrobe, M. M.: Clinical Hematology. Text Book. Lea and Febiger, 3rd Edition, 1952.
  14. Nossal, G.: Most killed vaccines in use termed not fit for a mouse. Medical Tribune, April 5, 1972.
  15. Ginter, E.: The Role of Ascorbic Acid In Cholesterol Metabolism. Research Institute of Human Nutrition, Bratislava, 1970.
  16. Klenner, F. R.: Massive doses of vitamin C and the virus diseases. Southern Med. Surg., 1951.
  17. Ginter, E.: Cholesterol and vitamin C. Amer. J. Clin. Nutr., 24:1238-1245, 1971.
  18. Mjasnikova, I. A.: O vlijaniji vodorastvorimych vitaminov na nekororyje storony obmena vescesty. Tr. Vojennomorskof medicinsk. akademiji Leningr., 8:140-148, 1947.
  19. Tjapina, L. A.: Vlijanie askorbovoj kisloty na cholesterinemiju pri giper toniceskoj bolezm i ateroskleroze. Gipertoniceskaja bolezn. Tr. AMN SSSR, 2:108-113, 1952.
  20. Spittle, C.: Atherosclerosis and vitamin C. Lancet, 11:1280-1281, 1971.
  21. Ginter, E.: Effects of dietary cholesterol on vitamin C metabolism in laboratory animals. Acta med. Acad. Sci Hung., 27:23-29, 1970.
  22. Ginter, E., Kajabal, I. and Nizner, O.: The effects of ascorbic acid on cholesterolemia in healthy subjects with seasonal deficit of vitamin C. Nutr. MetaboL, 12:76-86, 1970.
  23. Ginter, E., Bilisics, I. and Cerven, J.: Cholesterol metabolism under conditions of acute and chronic vitamin C deficiency in guinea pigs. PhysioL Bohemoslov., 14:466-471, 1965.
  24. Small, D.: Med. World News, March 30, 1971.
  25. Willis, G. C.: An experimental study of the intimal ground substance in atherosclerosis. Canad. Med. Ass. J., 69:17-22, 1953.
  26. Willis, G. C.: The Reversibility of Atherosclerosis. Canad. Med. Ass. J., 77:106-109, 1957.
  27. Duguid, J. B.: Pathogenesis of atherosclerosis. Lancet, 2:925, 1957.
  28. Shafer, C. F.: Ascorbic acid and atherosclerosis. Amer. J. Clin. Nutr., 23:27, 1970.
  29. Stamler, J.: Comprehensive Treatment of Essential Hypertensive Diseases. Monograph on Hypertension. Merck, Sharp and Dohme.
  30. Asahina and Asano: Prevention, July 1972. pp. 8 1-82.
  31. Mokranjac, M., Petrovic, C.: Report on mercury studies in guinea pigs in relation to amounts of vitamin C administered. C. R. Acad. Sci., Paris.
  32. Dannenberg, A. M. et al: Ascorbic acid in the treatment of chronic lead poisoning. JAMA, 114:1439-1440, 1940.
  33. Klenner, F. R.: The role of ascorbic acid in therapeutics. Tri-State Med. J., Nov. 1955.
  34. Anderson, E: W. et al: Carbon monoxide linked to heart disease. JAMA,22:5, July 1972.
  35. Pelletier, O.: Experiments with smokers and non-smokers. JAMA, April 1969.
  36. Mayers, B. W.: Where there’s smoke there may be carbon monoxide. Med. World News, Jan. 21, 1972.
  37. Chambers, R. and Pollock, H.: J. Gen. Physiol., 10:739, 1927.
  38. Hellne, G. and Helene, W.: EB virus in the etiology of infectious mononucleosis. Hosp. Practice, July 1970.
  39. Niderman, J. C.: College findings tie mono to EB virus. Med. World News, Dec. 1968.
  40. Schlegel, G. E. et al: The role of ascorbic acid in the prevention of bladder tumor formation. Trans. Amer. Ass. Genitourin. Surg., 61, 1969.
  41. Rous, S.: Urethritis in men. N. Y. Soc. Med., Dec. 15, 1971.
  42. Klenner, F. R.: Observations on the dose and administration of ascorbic acid when employed beyond the range of a vitamin in human pathology. J. Appl. Nutr., 23:3-4, 1971.
  43. Leuchtenberger, C. and Leuchtenberger, R.: New dangers seen in marijuana. Nature, Nov. 1971.
  44. Campbell, A. M. G. et al: Significant brain damage caused by smoking marijuana. Lancet, Dec. 1971.
  45. Virno, M. et al: Eye, Ear, Nose, Throat Monthly, 64, Dec. 1967.
  46. Hoffer, A.: Use of ascorbic acid with niacin in schizophrenia. Canad. Med. J., Nov. 6, 1971.
  47. Hawkins, D.: Back to reality the megavitamin way. Med. World News, September 24, 1971.
  48. Klenner, F. R.: Recent discoveries in the treatment of lockjaw with vitamin C and Tolserol. Tri-State Med. J., July 1954.
  49. Abrams, E. and Sandson, J.: Ann. Rheum. Dis., 27, 1964.
  50. McCormick, W. J.: Intervertable Disc Pathology: A new etiologic concept. Arch. Pre., 71:29, 1954.
  51. Greenwood, J.: Optimum vitamin C intake as a factor in the preservation of disc integrity. Med. Ann. D. C., 33:6, June 1964.
  52. Massell, B. F., Warren, J. E., Patterson, P. R. et al: Antirheumatic activity of ascorbic acid in large doses. New Eng. J. Med., 1950.
  53. Klenner, F. R.: Case history: Cure of a 4 year old child bitten by a mature Hiland moccasin with vitamin C. Tri-State Med. J., July, 1954.
  54. Klenner, F. R.: Case history: The black widow spider. Tri-State Med. J., Dec. 1957.

From Journal of the International Academy of Preventive Medicine, Spring 1974, Volume 1, Number 1, pp. 45-69
HTML Revised 23 March, 2003.
Corrections and formatting © 1999-2003 AscorbateWeb

SOURCE: http://www.seanet.com/~alexs/ascorbate/197x/klenner-fr-j_int_assn_prev_med-1974-v1-n1-p45.htm#Hellne-38

MECHANICS OF THE MATRIX


MARCH 25, 2012. We are witnessing an intensified effort, on the part of elite groups, to manage the Matrix.

This involves shaping:
political realities;
social realities;
economic realities;
medical realities;
information realities;
psychological realities;
spiritual realities.

When all is said and done, the attack is on the power and energy of the individual.

One part of my work consists in showing how the evolving medical cartel is really waging chemical warfare on the population, with toxic drugs. At the highest level, behind the curtain, the objective is to grossly weaken, physically and mentally, the body and the brain.

For example–
THE DEVASTATING TRUTH BEHIND OBAMACARE
National Health Insurance Before Supreme Court for Ruling

Last week, guest-hosting The Alex Jones Radio Show, I discussed the case of a young Michigan boy, whose parents have been taken to court three times to force them to submit their child to intensely toxic chemo treatments—despite these facts:

The boy’s latest scans reveal no sign of cancer; the drugs that would be forced on him can cause cancer; the drugs have not been approved to treat children.

And I warned: this is what waits for you and your children, up the line, if the Supreme Court allows Obamacare to stand as law.

The “share and care” humanitarian mask will be peeled away. The US Dept. of Health and Human Services will create, as mandated, a complete list of approved treatments for every disease-label under the sun. And everyone in the insurance plan (everyone in America) will be forced to take what the doctor tells them to take.

For a bonus, unapproved treatments will eventually be banned. People and practitioners who try to use alternative treatments will find themselves in trouble.
This is the hidden agenda of Obamacare. This is what it will morph into in the future—unless it is struck down as unconstitutional.

I’m not dreaming or fantasizing. I’ve been following and reporting on the medical cartel for 30 years, and I know the mindset of these people, these medical bureaucrats, these pharmaceutical string-pullers behind the scenes. Obamacare is right up their alley. It’s about control, so it’s an answer to their prayers.

What do we know about their mainstream medicine, the hospital-based drug-addled modern version?
On July 26, 2000, the Journal of theAmerican Medical Association published a landmark paper by Dr. Barbara Starfield (Johns Hopkins School of Public Health), “Is US health really the best in the world?” In it, Starfield revealed what many people inside the medical establishment already knew: every year, like clockwork, the medical system was killing huge numbers of people.

Each year in the US, as Dr. Starfield reported, there are:
12,000 deaths from unnecessary surgeries;
7,000 deaths from medication errors in hospitals;
20,000 deaths from other errors in hospitals; 
80,000 deaths from infections acquired in hospitals; 
106,000 deaths from FDA-approved correctly prescribed medicines.
The total of medically-caused deaths in the US every year is 225,000.

This makes the medical system the third leading cause of death in America, behind heart disease and cancer.

In the wake of Starfield’s devastating report, other facts came to light: 2.1 million people in America, every year, are hospitalized as a result of reactions to FDA-approved medicines.  Annually, 36 million serious adverse reactions to those drugs occur.

So, inclusive health coverage for many more Americans under the Obama Plan means these horrendous figures will rise.

This is the dirty secret. 

Obama and his allies are promoting a medical system that is the third leading cause of death in America.  It’s that stark and it’s that simple.

The Obama Plan involves appointing an “expert panel” to decide what treatments Americans should be given for what diseases, under the new regime.

Only a certified idiot would assume that, over time, alternative non-mainstream therapies would survive such an ongoing vetting.  Hope may spring eternal, but common sense makes it easy to grasp the realities on the ground. 

In the long run, alternative therapies will be edged out.  Those that remain will be permitted for a narrow range of conditions, or as adjuncts to standard drug treatments and surgery. 

Chiropractors and acupuncturists, who are temporarily basking in the notion that Obama “really cares,” are in for a very rude awakening. Their careers and practices will be significantly reduced.  Not today, not tomorrow, but it will happen. 

Doctors, under the Plan, will be telling patients they may not take nutritional supplements while in treatment.  This will assume the status of an irreversible edict.  In many cases, “while in treatment” means years. 

What happens to a person, conscripted into the mandated Plan, who is told by his doctor that he should/must receive a vaccine?  Suppose this person says no?  What are the consequences?  Will he then be labeled a defector?  What penalties will he suffer? 

Does a diagnosis of cancer imply a patient must submit to chemotherapy, radiation, and surgery?  Can these treatments be forced upon him?

Perhaps, in the early days of the Plan, nothing untoward will happen.  But then, as time passes, and the system assumes tighter and tighter controls, the hand of government will close around the recalcitrant patient’s neck.

Take this vaccine. Take this chemo drug. If you don’t, you’re out of the system, and that makes you a criminal, because everyone has to be in the system.”

Doctors, who are an integral part of the Plan, will surely be punished if they give unapproved (alternative) treatments to patients.   

And in order to make the Plan operate on a day-to-day basis, the records and bookkeeping data of every health-care practitioner in America will be tracked on government computer networks. 
Every person in America will have a traceable and trackable medical ID package. Government-issued.  There is no way around it.  The monitoring apparatus can’t work without it.

Orwellian consequences lie up the road in the field of psychiatric practice.  In case you hadn’t noticed, the invention of “disorders” by committee is the preferred method for “discovering” more and more mental illnesses. 

Yet, the science is completely fraudulent.  For evidence, consult the many works of psychiatrist Peter Breggin, who has done more than any other person to expose the guts of his own profession. (www.breggin.com)  Breggin establishes that mental disorders are not authoritatively diagnosed by a chemical or biological test.  Conclusive tests do not exist.  And worse, in this undefined and arbitrary territory, the drugs that follow diagnoses are killers: for example, 300,000 cases of motor brain damage, as a result of the administration of major tranquilizers.

Under the Obama Plan, you can bet your bottom dollar that psychiatric care will eventually become mandatory.  A patient suddenly diagnosed with clinical depression or bipolar disease will be told he must take the drugs—and suffer their adverse effects.   

Very young children will be given more and more debilitating and dangerous brain drugs.
Under the Obama Plan, it will be very convenient to declare new pandemics every few seasons, because these phony non-epidemics provide an opportunity to herd the sheep into clinics and remind them who is running the show. Go here, take this vaccine; go there, take that drug; the epidemic is endangering the herd, and you must help your brothers and sisters.

These are the figures on the last several “epidemics.”  They are not yearly; they are grand totals, to date; global totals, except in the case of West Nile (US only):
SARS: 774 deaths.
WEST NILE: 1159 deaths.
BIRD FLU: 262 deaths.
SMALLPOX: (terrorist threat): 0 deaths.
SWINE FLU:  25,000 deaths.

To give perspective, globally, 250 thousand to 500 thousand people die of ordinary flu-like illness every year.  Yet this higher death rate accrues no interest as an epidemic.  It is only the “teaching (brainwashing) moments” of the phony epidemics that are promoted by health agencies (e.g., CDC and WHO) and their pharmaceutical allies, who rake in billions by manufacturing new vaccines.

Yes, under the Obama Plan, there will be more declared health emergencies, and they will serve to cement the citizen to his new role as eternal patient in the medical march along bleak streets of the future.

Can you perceive the loss of individual freedom implicit in this universal system of health control?
_________________________________

Sources and comments:  I’m fully aware that people reading the facts in this essay will be shocked, and they will have doubts.  Here are the sources for those facts.  Things are not what they seem.
Barbara Starfield, “Is US health really the best in the world?”  JAMA, July 26, 2000.  Contains statistics on medically-caused deaths in the US.

On January 8, 2001, the LA Times ran a piece by Linda Marsa on the effects of medical drugs in the US.  Predictably, the story sank like a stone.  It provoked no Congressional hearings, no arrests. 
The article described, in a few key paragraphs, a world of trouble.  Adverse medical events, from med drugs:

A 1998 University of Toronto study found that roughly 100,000 Americans die of adverse [medical-drug] reactions each year, and 2.1 million more are hospitalized.”

Marsa offered, in her Times article, a quote from an associate professor of medicine at Harvard, Dr. David Bates, an author of a 2000 study on drug effects.  The study found that “18 percent of patients complained of drug-related complications,” Marsa wrote.

Here is the quote from Dr. Bates:  “People often have [drug-caused] symptoms for months, but they’re either reluctant to let their doctor know or they weren’t sure if they just felt lousy…But these numbers translate to 36 million adverse drug events per year.”

To add up the death totals from recent phony epidemics:

SARS—See WHO “Summary of probable SARS cases with onset of illness from 1 November 2002 to 31 July 2003” (based on data as of Dec.31, 2003).

BIRD FLU—See WHO “Confirmed Human Cases of Avian Influenza A (H5N1)” (24 September 2009)

WEST NILE—See CDC, West Nile Virus, Statistics, Surveillance, and Control.  Years are reported separately, 1999-2009.  I included only US cases because I couldn’t find a good source for global cases.

To confirm that every year, between 250,000 and 500,000 people die from ordinary flu, see WHO Fact Sheet No.211, Influenza (Seasonal).

Read Dr. Peter Breggin’s classic, Toxic Psychiatry, St. Martin’s Press, 1991.  Follow Breggin’s argument, through several chapters; labeled mental disorders are not based on factual biological evidence; and see p.89-91 for evidence that at least 300,000 people are suffering from brain damage (tardive dyskinesia) as a result of being administered major tranquilizers.

Founded in 1992, the National Center for Complementary and Alternative Medicine (NCCAM), a minor bureau of the National Institutes of Health (a federal agency), has managed to derail, stall, and divert the progress of real alternative medicine.  It has forwarded no breakthroughs.  It has bogged itself down in conferences, reports, and committee deliberations.  It has fooled a number of so-called alternative-health advocates into believing that the federal government supports non-mainstream health strategies. 

Imagine what would happen when healthcare in this country becomes centralized to a much greater degree under the Obama Plan.  If this one tiny agency, NCCAM, can now befuddle the alternative field with a collection of inept and self-seeking bureaucrats, gargantuan power held at the top of the federal government will make that diversion look like a raindrop in a hurricane.

The history of the decline of infectious disease is a history of improved sanitation, alleviation of overcrowding, the rise of the middle class, and above all, the betterment of nutrition.  This decline in disease occurred before the introduction of antibiotics and widespread vaccination. (See Ivan Illich, Medical Nemesis)  Under massively centralized medical care, in an environment where chemically saturated agri-business grows our food in depleted topsoil, there is a greater and greater need for nutritional supplements.  But this vital avenue will be narrowed and blocked in the ways I have indicated above. 

Last but not least, medical-research fraud continues unabated, an out-of-control rampant crime. 
See, for example, “20 Percent Of Cancer Studies Report Conflict of Interest,” ScienceDaily (May 13, 2009): “Nearly one-third of cancer research published in high-impact journals disclosed a conflict of interest, according to a new study from researchers at the University of Michigan Comprehensive Cancer Center…”

Also, from the Boston Globe (Boston.com, August 15, 2005), “Flaws are found in validating medical studies; many see need to overhaul standards for peer review”: 

“…after a study that sent reverberations through the medical profession by finding that almost one-third of top research articles have been either contradicted or seriously questioned, some specialists are calling for radical changes in the system…almost one-third of the top papers that appeared in top journals over a 13-year period from 1990 to 2003, had been either contradicted or found to have potentially exaggerated results. All the articles had [prior to publication] undergone vigorous peer review, leading to questions about whether problems should have been caught by reviewers…”

What does this epidemic of cheating and lying in medical research add up to? New dangerous drugs will continue to be approved for public use, by the government. The dangers of the drugs will be hidden in fabricated studies published in prestigious journals. 

As the Supreme Court deliberates on whether the individual mandate in Obama’s healthplan implies a penalty or tax if people opt out, and as the Court mumbles its way through questions about the Commerce Clause of the Constitution—which was never written to permit Congress to command people to buy health insurance—the real secret is concealed.

This insurance plan will capture more and more of the population in the cross-hairs of chemical warfare. No amount of squirming or arguing is going to change that. 

Jon Rappoport is the author of a new collection, THE MATRIX REVEALED. Jon has worked as an independent investigative reporter since 1982.  The LA Weekly nominated him for a Pulitzer Prize, for a interview he did with the president of El Salvador University, where the military had taken over the campus and was disappearing students and burning books.  He has written for In These Times, Village Voice, LA Weekly, Spin Magazine, CBS Healthwatch, Stern.  His work can be found at www.nomorefakenews.com
qjrconsulting@gmail.com


Monday, March 26, 2012

Feeding the PINEAL GLAND

Foods that Feed The Pineal Gland


Our pineal gland otherwise known as our master gland or the gland that governs over our third eye is the center of psychic awareness in the human mind. It is about the size of a pea and sits inside a cave located behind the pituitary gland. It naturally produces a hormone called melatonin which regulates human daily body rhythms that deal directly with the day and night cycles. Developing and expanding the function and the energy of your pineal gland is extremely important as it affects every system in your body physically and it has the potential to determine the expansion or the contraction of your psychic awareness, consciousness, and experience. Sunlight is extremely important for the pineal gland and yes sunlight is a form of food as food is any substance that nourishes the body. Sunlight can be taken in and digested through the eyes, skin, hair, nose hairs, and ears and should be consumed for at least 30 minutes a day. To fully engage the pineal gland, sunlight should be taken in through the pupils.

Seaweed vegetables that are sun-dried by the sun contain high amounts of vitamin D, many vitamins in the B-vitamin family and iodine. Those vegetables include and are not limited to kombu, arame, wakame, dulse, nori, etc.
Dark leafy greens like our kale, turnip greens, mustard greens, bok choy, collard greens etc are extremely nourishing for the pineal gland as this gland absorbs the properties of the green color of the vegetables and properly distributes them to the appropriate systems of the body so that the body is thoroughly nourished.

Consuming meats including fish that has high amounts of mercury, carbonated beverages, fluoride in our water and our toothpaste and access to smog negatively affect the pineal gland and can block its ability to function properly. When you consume meat from an animal, you are ingesting the DNA of that animal and therefore taking on the negative and positive experiences of an animal which could interrupt the ability of the pineal gland to take on its own psychic awareness blueprint of the individual.

The proper foods can positively affect your pineal gland but you can also activate your pineal gland by eating more of a raw foods, vegan, or vegetarian diet, running an ozone machine in your home to clean up the air in your home, and drinking filtered water. As much as the pineal gland needs sunlight, it also needs to produce enough serotonin to be activated so that it can increase its psychic awareness therefore serotonin is produced when the brain is asleep and therefore sleeping in a very dark room is extremely nourishing for the pineal gland as well. Foods that produce serotonin are almonds, bananas, hot peppers, rice, potatoes, and black-eyed peas and when consumed can also nourish and feed the pineal gland as well.

WANT TO USE THIS ARTICLE IN YOUR E-ZINE OR WEB SITE? You can, as long as you include this complete blurb with it:
Nwenna Kai is the author of The Goddess of Raw Foodsavailable for purchase at www.amazon.com and the upcoming children’s book, The MoreLove’s coming September 2010. You can get the FREE e-book Nwenna Kai’s Holiday Recipes at her website www.nwennakai.com by signing up for her weekly e-newsletter at her website. She is the previous owner of Taste of the Goddess Cafe, one of LA’s pioneering organic raw food cafes. She is the 2007 winner of the Elizabeth Dole Young Entrepreneurial Scholarship sponsored by Women Impacting Public Policy (WIPP) for her work as a health and wellness entrepreneur. Visit her website at www.the-guide-to-raw-foods.com and her blog at www.theguidetorawfoods.com/blogspot.com.

Source:  http://2012indyinfo.com/2012/03/25/the-guide-to-raw-foods-foods-that-feed-the-pineal-gland/


Sunday, March 4, 2012

Louis Pasteur vs. Antoine Bechamp

Know the True Causes of Disease

Mainstream medicine believes that virtually all illness is caused by germs or genetic hereditary weakness, as well as deformities and trauma injuries. Their solution and strategy is to have us believe that there are over 10,000 different diseases and that each of these diseases requires outside intervention from drugs and surgery. The truth is that most illness is due to cellular malfunction caused by cellular toxicities and cellular malnutrition, both of which can be avoided and overcome naturally.

It was Louis Pasteur, the so-called "father of modern germ theory" so widely revered by mainstream medicine, who was largely responsible for germ theory being a primary precept of today`s medical practice. Few people are aware of the controversy which surrounded Pasteur in his early days or of the work of a more esteemed contemporary whose works Pasteur plagiarized and distorted. That contemporary was fellow French Academy of Sciences member Antoine Bechamp, one of France`s most prominent and active researchers and biologists whose theories and research results stood in stark opposition to Pasteur`s germ theory.

Pasteur essentially dug up the germ theory of disease and put his name on it. It wasn`t a new idea. The concept, which theorizes that many diseases are caused by germs, had actually been outlined by other people many years before. Pasteur nevertheless claimed to have "discovered" germs. Bechamp, on the other hand, proved through original research that most diseases are the result of diseased tissue and that bacteria and viruses are largely after-effects instead of causes of disease.

Antoine Bechamp was able to scientifically prove that germs are the chemical by-products and constituents of pleomorphic microorganisms enacting upon the unbalanced, malfunctioning cell metabolism and dead tissue that actually produces disease. Bechamp found that the diseased, acidic, low-oxygen cellular environment is created by a toxic/nutrient deficient diet, toxic emotions, and a toxic lifestyle. His findings demonstrate how cancer develops through the morbid changes of germs to bacteria, bacteria to viruses, viruses to fungal forms and fungal forms to cancer cells.

After some initial controversy, Pasteur`s germ theory ended up winning the day with mainstream medicine - owing in large part to the fact that the theory enabled mainstream medicine to hugely profit from the patented drugs and treatments for fighting germs. After all, had Bechamp`s discoveries been incorporated into current medical curriculum, it would likely have meant a virtual elimination of disease and the end of the pharmaceutical industry.

The germ theory of medicine stands in stark contrast to thousands of years of man looking to nature to nourish and heal it, dating back to ancient Chinese medicine which treated the whole body instead of the symptoms of illness. As Hippocrates, "the father of medicine" observed 2400 years ago, "Nature is the physician of man." Hippocrates also advised, "Leave your drugs in the chemist`s pots if you can cure your patient with food."

Though mainstream medicine might have us believe otherwise, the simple truth is that no one ever became ill due to a deficiency in pharmaceutical drugs. Lack of nutrition combined with exposure to toxins is what causes us to become ill.

Someday, germ theory and unnatural drugs will be relegated to the science junk pile where they belong and man will re-discover the value of eating a nutrient-dense organic diet, avoiding toxins and nutritional deficiencies and living a healthy lifestyle. When that happens, the words of Thomas Edison may prove to be a welcome prophesy:

"The doctor of the future will give no medicine but will interest his patients in the care of the human frame, in diet and in the cause and prevention of disease."